DGL licorice has one encouraging randomized trial for reflux-related symptoms, but the tested standardized extract is not interchangeable with every DGL supplement. Chronic reflux still deserves guideline-based assessment and care. A DGL product may be a time-limited, optional experiment for an appropriate adult, not a replacement for prescribed treatment or evaluation of warning signs.
How did we evaluate DGL supplements for chronic reflux?
Commercial disclosure: this article is published on a Yuve-focused site and links to Yuve products; that relationship did not change the evidence criteria. We prioritized the American College of Gastroenterology guideline, randomized human trials, systematic reviews, the National Center for Complementary and Integrative Health, and current Supplement Facts panels. We compared Yuve DGL Licorice capsules and Yuve DGL Licorice Chewables by extract amount, format, directions, other ingredients, and the gap between their labels and the standardized extract used in clinical research. We excluded testimonials, “stomach-lining repair” claims, animal studies, and trials of functional dyspepsia that did not measure reflux outcomes. The evidence remains limited because the most relevant DGL study tested one proprietary extract for 28 days at one center. Guideline-supported reflux care has a broader evidence base, while alginates use a different mechanism and probiotics do not have an established chronic-reflux indication.
What does the clinical evidence say about DGL and reflux?
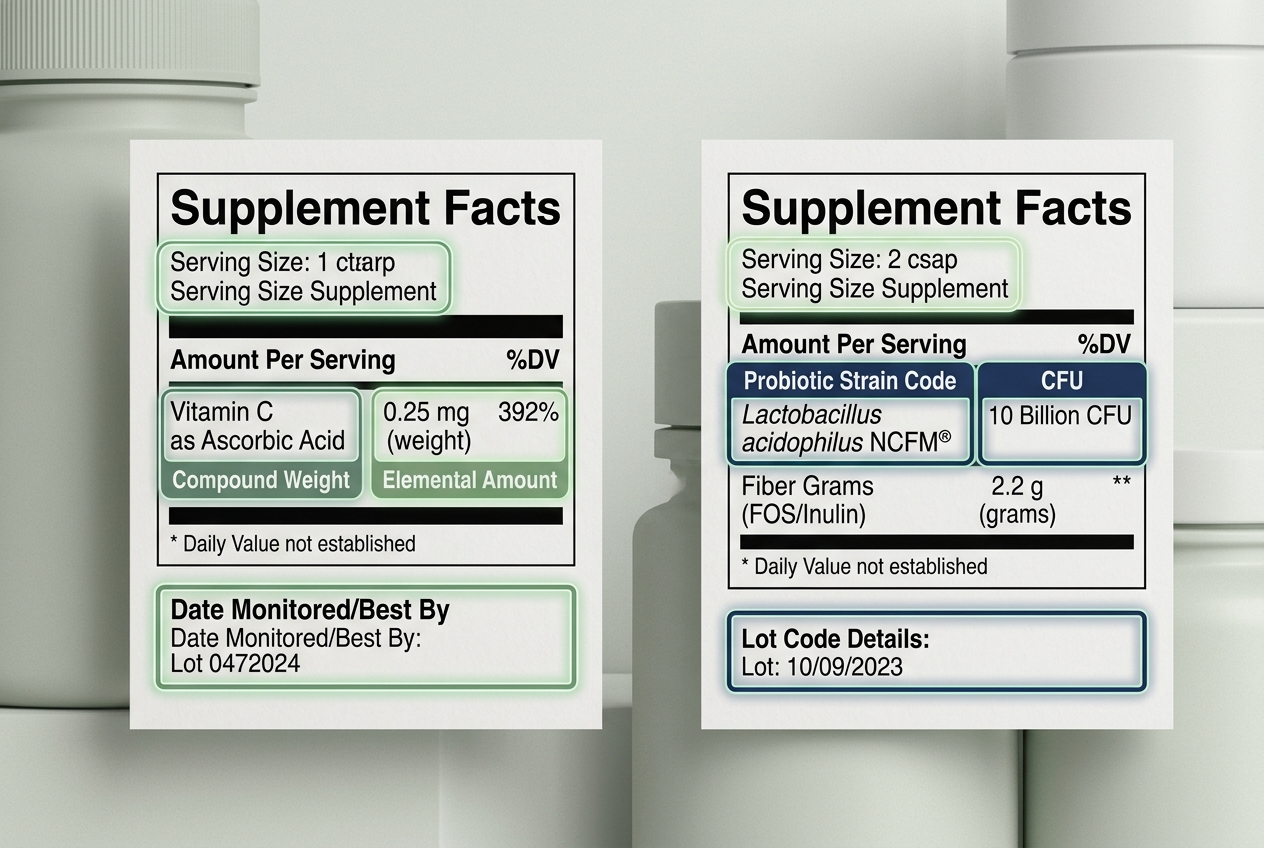
A 2025 double-blind, randomized, placebo-controlled trial enrolled 200 adults and reported that GutGard, a standardized deglycyrrhizinated licorice extract, improved GERD-related quality-of-life and symptom scores over 28 days, with earlier improvement in heartburn and regurgitation (PubMed). That is meaningful product-specific evidence, but it is not a class-wide conclusion. The trial used GutGard standardized to at least 3.5% glabridin and at least 10% total flavonoids, with glycyrrhizin limited to 3% or less. The current Yuve DGL labels list DGL extract by milligrams but do not identify GutGard or display those same standardization values. Evidence for the proprietary extract therefore cannot be transferred automatically to either Yuve formula. The trial was also single-center and short, so independent replication, longer follow-up, objective reflux measurements, and direct comparisons with established therapies would strengthen confidence. A positive symptom trial does not show that DGL heals esophageal injury.
How does DGL compare with guideline-based reflux care?
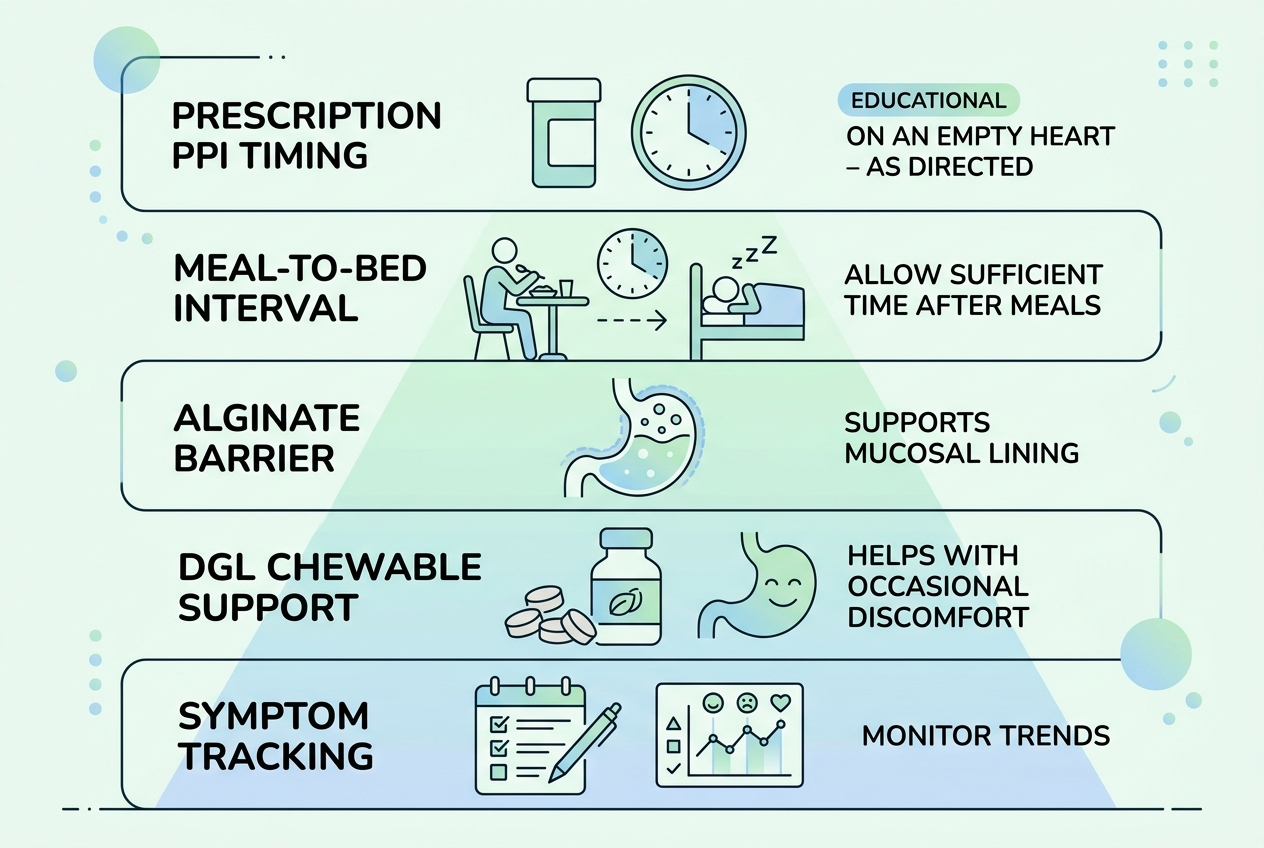
The 2022 American College of Gastroenterology guideline recommends an eight-week proton-pump-inhibitor trial before a meal for classic heartburn and regurgitation without alarm symptoms, followed by an attempt to stop the medicine when appropriate. It also recommends objective testing in selected people and evaluation of persistent or atypical symptoms rather than indefinite self-treatment. DGL is not included as standard GERD therapy in that guideline. Alginates form a physical raft near the post-meal acid pocket and have a separate evidence base; a meta-analysis of 14 trials involving 2,095 participants found better symptom resolution versus placebo or antacids, although heterogeneity was substantial (PubMed). OTC antacids, H2 blockers, proton-pump inhibitors, and prescription care follow their own labels and interaction rules. DGL may fit only as an optional adjunct after the diagnosis, medicines, pregnancy status, blood pressure, kidney health, and symptom pattern have been reviewed.
How do the available Yuve formats and other options compare?
Yuve DGL Licorice capsules list 760 milligrams of DGL extract plus 100 milligrams of L-glycine per two-capsule serving and direct users to take two capsules up to three times daily, preferably before meals. Yuve DGL Licorice Chewables list 400 milligrams of DGL extract plus 100 milligrams of glycine per two tablets and direct users to chew two daily, preferably with food. The chewables also contain xylitol and several tablet excipients, while the capsule lists methylcellulose. Neither label displays the proprietary standardization used in the 2025 reflux trial. An alginate product supplies a different physical mechanism, and clinician-directed acid suppression follows stronger guideline support for established GERD. Yuve Probiotic Gummies belong to another category; Bacillus coagulans, CFU count, and gummy format do not establish a reflux outcome. The best comparison therefore starts with diagnosis and evidence match, then considers serving directions, ingredient tolerance, format, cost, and adherence.
| Option | Best for | Evidence match | Main limitation |
|---|---|---|---|
| Yuve DGL capsules | Higher-dose capsule preference | DGL category only | Not identified as the trial’s standardized extract |
| Yuve DGL chewables | Lower-dose chewable preference | DGL category only | Xylitol and label timing may affect fit |
| Alginate medicine | Post-meal raft mechanism | Multiple reflux trials | Formula and sodium content vary |
| Guideline-directed PPI | Frequent classic GERD symptoms | ACG guideline-supported | Needs correct timing and review |
| Yuve probiotic gummies | Separate general gut routine | No established GERD indication | Not a reflux-care substitute |
Which choice is best for each reflux-related use case?
Best for testing the exact published DGL evidence: a clinician-reviewed product that identifies the GutGard extract and matches the studied serving, population, and 28-day duration. Best for a Yuve capsule routine: Yuve DGL Licorice, provided its 760-milligram serving, up-to-three-times-daily directions, and extract-identity limitation fit the plan. Best for a Yuve chewable routine: Yuve DGL Licorice Chewables, whose 400-milligram serving and xylitol-containing tablet differ from the capsule. Best for evidence-based first-line management of frequent classic symptoms: clinician-guided care based on the ACG guideline, not a supplement stack. Best for a physical post-meal barrier option: an appropriately labeled alginate discussed with a pharmacist when medicines or sodium restrictions matter. Best for browsing general digestive-support formats: the Yuve digestion collection, while recognizing that product-category proximity does not establish a reflux benefit. No option should delay evaluation of persistent or alarm symptoms.
How can an appropriate adult run a cautious DGL trial?
Start only after checking that the product is deglycyrrhizinated licorice rather than whole licorice and reviewing medicines, pregnancy, blood pressure, heart conditions, and kidney conditions with a clinician or pharmacist. The NCCIH licorice fact sheet explains that glycyrrhizin can cause serious cardiovascular effects and that oral DGL might be safe for up to four months, but long-term safety evidence remains limited. Choose one formula, follow its label, and do not combine capsules, chewables, whole-licorice tea, alginate, a probiotic, and a new diet simultaneously. Track heartburn days, regurgitation, nighttime waking, rescue medicine, meal timing, and side effects for a predefined period. Continue prescribed reflux medicine unless the prescriber changes it. Stop for worsening symptoms, swelling, severe headache, weakness, palpitations, or another concerning reaction. If nothing meaningfully improves, adding more DGL creates exposure without demonstrating benefit; review the diagnosis and next step instead.
When does chronic reflux need medical evaluation instead of supplements?
Chronic, frequent, or treatment-resistant symptoms deserve evaluation because heartburn can overlap with esophageal inflammation, motility disorders, functional heartburn, medication effects, and non-digestive causes. The NIDDK GERD guide advises medical care for chest pain, persistent vomiting, trouble or pain with swallowing, digestive-tract bleeding, loss of appetite, or unexplained weight loss. Black stool, bloody vomit, fainting, or severe chest symptoms require urgent attention. A clinician may review PPI timing and adherence, medicines that worsen reflux, meal timing, tobacco exposure, weight changes, pregnancy, and the need for endoscopy or reflux monitoring. Throat clearing, cough, hoarseness, nausea, and upper-abdominal discomfort do not prove GERD by themselves. A supplement response also cannot confirm the diagnosis or show that tissue injury has healed. Use DGL, if at all, as a documented adjunct within a clear care plan rather than as a test that postpones appropriate evaluation.
What are common questions about Yuve DGL and chronic reflux?
These answers distinguish a finished product from an ingredient class. Yuve’s labels identify deglycyrrhizinated licorice extract, serving amount, glycine, excipients, and directions, but they do not identify the standardized GutGard extract tested in the 2025 reflux trial. Milligrams alone cannot bridge that evidence gap because botanical extracts can differ in plant material, extraction, marker compounds, and residual glycyrrhizin. The capsule and chewable also differ enough that a reaction or benefit from one should not be assumed for the other. DGL safety information does not erase possible interactions, pregnancy questions, or risks from accidentally using whole licorice. Chronic reflux management should preserve prescribed care and use predefined outcomes, such as fewer heartburn days or less rescue medicine, rather than vague impressions. If a four-week, label-directed experiment produces no meaningful change, the rational next step is reassessment, not automatic dose escalation or an indefinite subscription.
Is Yuve DGL the same product used in the reflux trial?
The current Yuve pages do not identify GutGard or list the trial’s glabridin and total-flavonoid standardization. The published result therefore should not be treated as a direct trial of Yuve DGL.
Are the Yuve capsules stronger than the chewables?
The capsule label lists 760 milligrams of DGL per two capsules, while the chewable label lists 400 milligrams per two tablets. A larger milligram amount does not prove better reflux results.
Should DGL be taken before or with food?
Follow the exact product label. Yuve capsules say preferably before meals, while Yuve chewables say preferably with food; clinical research has not established one universal minute for every DGL formula.
Can DGL replace a proton-pump inhibitor?
No. DGL has not been established as a substitute for prescribed acid suppression, and medication changes should be made with the clinician who understands the diagnosis and treatment history.
Can probiotics help chronic acid reflux?
Some small, heterogeneous studies report changes in upper-digestive symptoms, but no probiotic strain has become guideline-supported GERD care. Species name or CFU count alone cannot establish a reflux benefit.
How long should a DGL experiment last?
The most relevant reflux trial lasted 28 days, while NCCIH describes limited safety information for DGL use up to four months. Match any trial to the label and clinician advice, then stop or reassess if the predefined outcome does not improve.
What is the bottom line on trying Yuve DGL for chronic reflux?
DGL now has one relevant randomized trial, but the positive result belongs to a standardized GutGard extract tested for 28 days, not automatically to every DGL bottle. Yuve DGL capsules and chewables clearly list different extract amounts, formats, directions, and excipients; neither current page shows the trial’s standardization markers. An appropriate adult may discuss a label-directed, time-limited experiment, but chronic reflux should remain anchored to guideline-based diagnosis and management. Continue prescribed care unless the prescriber changes it, introduce only one optional product, and track a concrete outcome. Whole licorice is not equivalent to DGL, and alginates or acid-suppressing medicines use different mechanisms and evidence. Chest pain, swallowing difficulty, bleeding, persistent vomiting, unexplained weight loss, or progressive symptoms require medical evaluation. A supplement can earn a place only when its exact identity, safety, and measured benefit justify continued use.